
What Is a Corpectomy? Spine Surgery Explained
Corpectomy, in plain terms: A corpectomy is spine surgery that removes a vertebral body, the main block of bone in a spinal segment, to take pressure off the spinal cord or nerves. The surgeon then rebuilds the gap with a bone graft or cage and fuses the segment with hardware. It can be done in the neck, mid-back, or lower back.
If a surgeon has used the word corpectomy, it helps to understand what it means before you weigh any decision. "Corpus" means body and "ectomy" means to remove, so a corpectomy removes the body of a vertebra. It is the operation chosen when the thing pressing on the spinal cord is built into the bone itself, out of reach of a simpler disc surgery, or when a vertebra has been damaged by a fracture, tumor, or infection and has to come out. This guide is the plain-English overview: what a corpectomy is, the conditions it treats, the different types by region, how it compares with the other spine surgeries people confuse it with, and what risks and recovery look like, with links to deeper guides on each.
- A corpectomy removes an entire vertebral body (and the discs beside it) to decompress the spinal cord or nerves, then rebuilds and fuses the spine with a graft or cage and hardware.
- It does two jobs in one operation: decompression (taking pressure off neural structures) and reconstruction (restoring a stable, aligned spine).
- It is used when compression or damage sits in the vertebral body itself, not just at the disc, from multilevel stenosis, bone spurs, a hardened ligament, a retrovertebral disc, fracture, tumor, or infection.
- It can be performed in the cervical, thoracic, or lumbar spine, and the region decides the approach and the reconstruction.
- It is more extensive than a discectomy or a laminectomy, which is why it is reserved for problems those smaller operations cannot reach.

What's in This Guide
How a Corpectomy Works
However it is described, a corpectomy follows one logic: reach the vertebral body, remove it along with the discs above and below, clear away whatever is pressing on the spinal cord or nerves, then rebuild the gap and fuse the segment so the spine stays stable. The surgical approach changes with the region of the spine, but the core sequence stays the same.
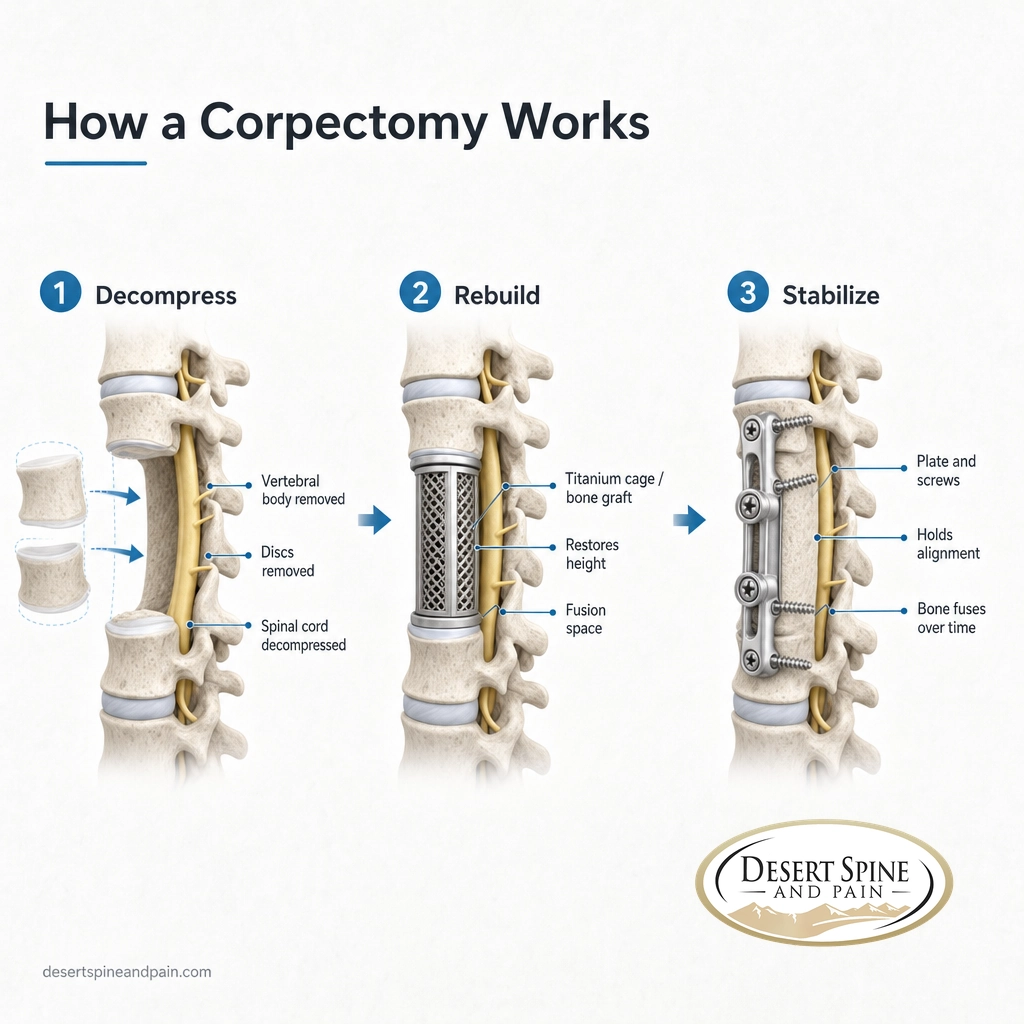
- Decompress. Under general anesthesia, the surgeon opens a protected path to the spine, removes the discs on either side and then the vertebral body itself, and clears any bone spurs, hardened ligament, disc fragment, tumor, or infected bone sitting against the neural structures.
- Rebuild. Removing a vertebral body leaves a space that has to be filled. The surgeon bridges it with a strut of bone (from the patient or a donor) or a titanium or PEEK cage packed with graft material.
- Stabilize. Hardware (a plate, or screws and rods) is fixed across the segment to hold everything steady while the bone grows together. Over months, the graft and the neighboring vertebrae fuse into one solid unit.
A helpful way to picture it: the surgeon removes a damaged pillar, clears the space behind it, sets a new pillar in place, and braces it until the bone heals around it. Because it decompresses and reconstructs at once, a corpectomy solves two problems in a single operation. For the step-by-step neck version, see our guide to how a cervical corpectomy works, and for the all-regions procedure walkthrough, see the vertebral corpectomy procedure and purpose.
Source: Columbia Neurosurgery corpectomy overview | University of Maryland Medical System corpectomy patient guide
When a Corpectomy Is Needed
At Desert Spine and Pain, the philosophy is the least invasive effective treatment first, and most spine problems never need surgery at all. A corpectomy becomes the right tool only when the vertebral body is the source of the problem, either by pressing on the spinal cord and nerves or by being so damaged that it must be removed. The usual reasons include:
- Multilevel spinal stenosis with myelopathy. When degenerative narrowing and bone spurs compress the spinal cord across more than one level, a corpectomy can decompress the whole span at once.
- Large bone spurs (osteophytes) that project from the back of a vertebral body into the spinal canal.
- A hardened posterior longitudinal ligament, where the ligament behind the vertebral bodies turns to bone and presses on the cord.
- A disc fragment that has migrated behind the vertebral body, out of reach of a standard discectomy.
- Fracture, tumor, or infection that has destroyed or invaded the vertebral body and must be removed to relieve pressure and restore stability.
Much of the degenerative cord compression a corpectomy addresses in the neck is called cervical spondylotic myelopathy, which the medical literature describes as the most common cause of spinal cord dysfunction in adults over 55 in North America. That matters for a reason many patients find reassuring: not every tight-looking scan needs surgery.
Myth: "Back pain or a worn-looking scan means I need a corpectomy." It does not. Wear-and-tear changes show up on imaging in huge numbers of people who feel fine, and ordinary back or neck pain is almost never a reason for this surgery. A corpectomy treats true, symptomatic compression coming from the vertebral body, confirmed by your symptoms, your neurological exam, and your images read together, never by a scan alone.
For the full range of problems that can lead here, see the Desert Spine and Pain overview of spine conditions and its surgical options for spinal stenosis.
Source: American Academy of Family Physicians: Cervical Spondylotic Myelopathy | Columbia Neurosurgery: indications for corpectomy
Types of Corpectomy by Spine Region
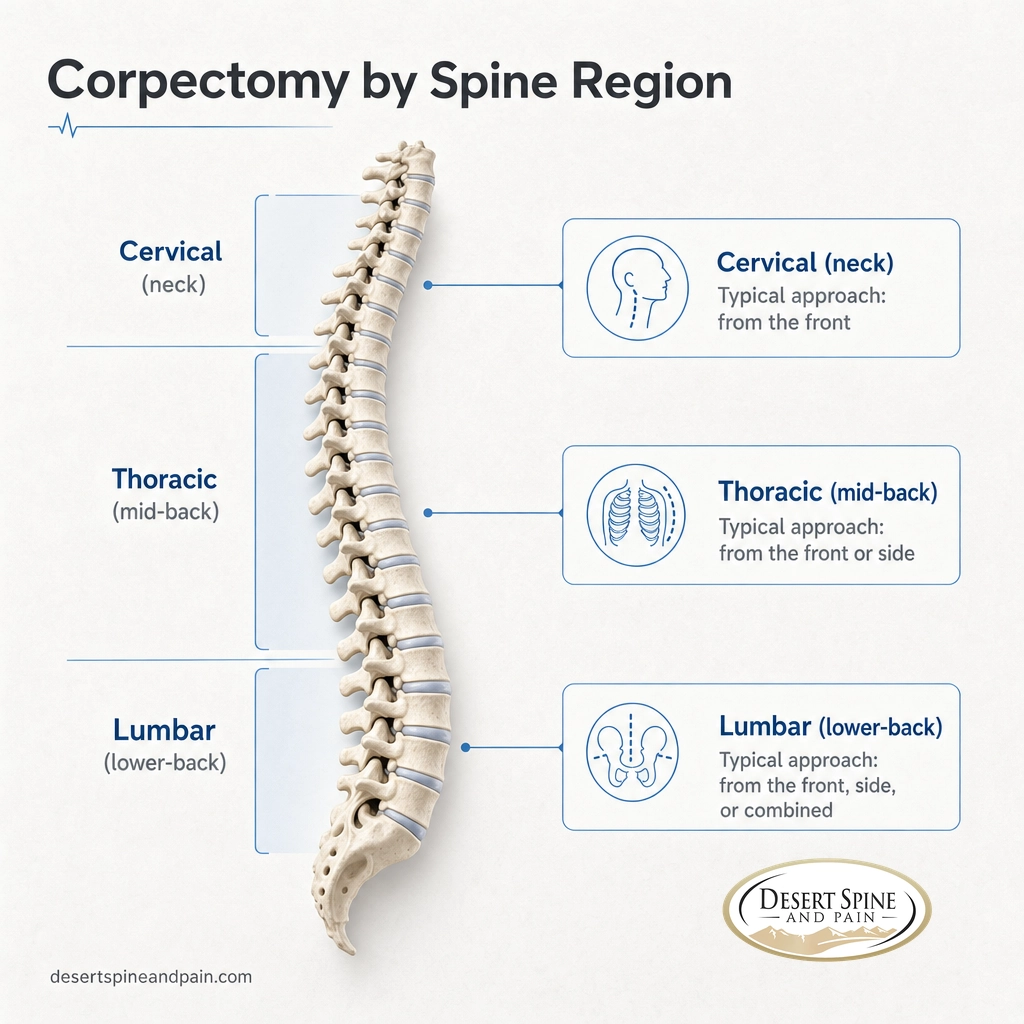
Corpectomy is a family of operations rather than one fixed procedure. The same core steps apply wherever it is done, but the region of the spine shapes the approach, the reconstruction, and the most common reason for surgery. Surgeons also describe a corpectomy as single-level or multilevel, depending on how many vertebral bodies have to come out.
| Region | Where | Typical approach | Common reasons |
|---|---|---|---|
| Cervical | Neck | Usually from the front (anterior) | Multilevel stenosis with myelopathy, bone spurs, hardened ligament, retrovertebral disc |
| Thoracic | Mid and upper back | Often from the front or side | Fracture, tumor, infection, degenerative compression |
| Lumbar | Lower back | Front, side, or combined | Burst fracture, tumor, infection, severe degeneration |
The cervical spine is the most common setting for a corpectomy, because degenerative narrowing and cord compression are frequent in the neck. For the neck-specific version, including the anterior approach and how it compares with an ACDF, see our detailed guide to how a cervical corpectomy works. For the all-regions procedure in full, read the vertebral corpectomy procedure and purpose. Because a corpectomy always pairs decompression with a fusion, it is sometimes combined with a decompression from the back of the spine for very tight or multilevel compression.
Source: Columbia Neurosurgery: thoracic corpectomy | University of Maryland Medical System: corpectomy patient guide
Corpectomy vs. Other Spine Surgeries
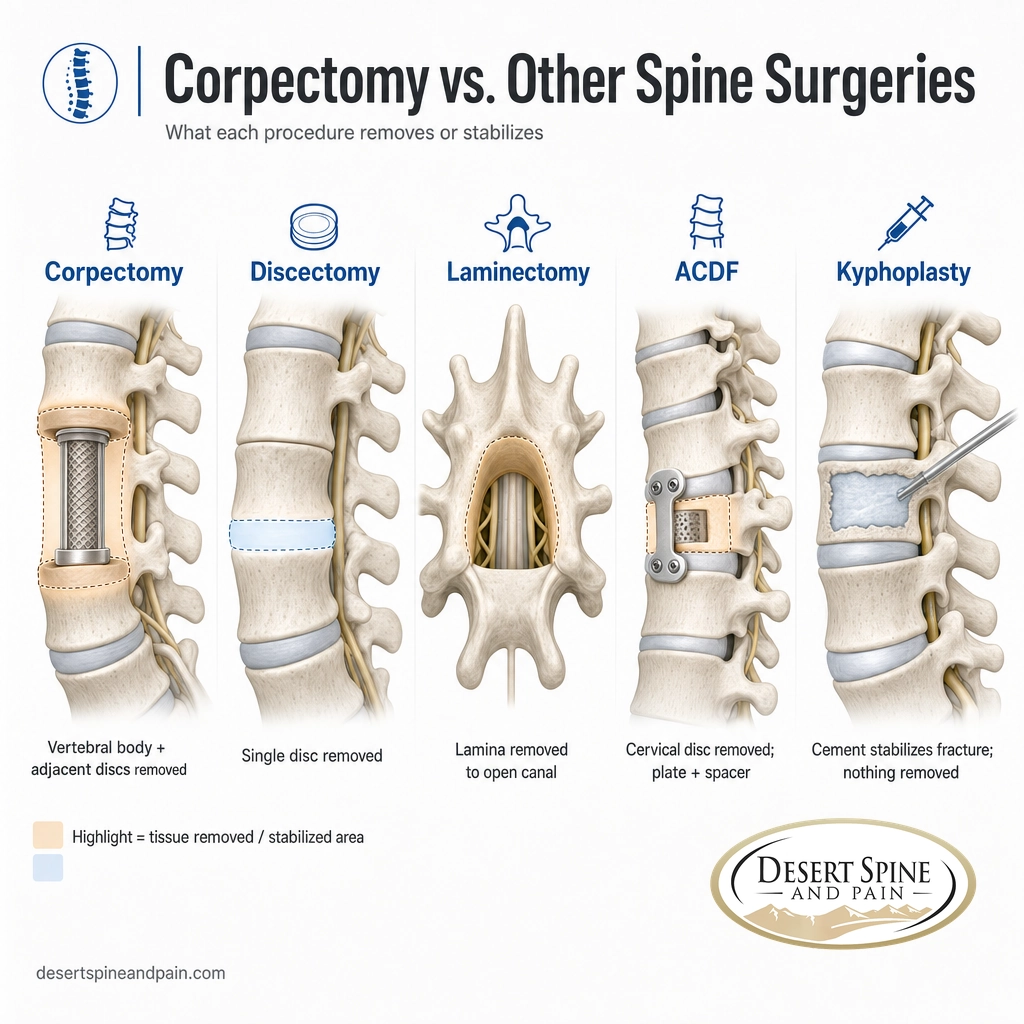
The word corpectomy is easy to mix up with the other spine operations, because several of them are done nearby and most end in a fusion. The real difference between them is simple once you see it side by side: each surgery removes a different part of the spine, chosen by where the pressure or the damage actually sits.
| Procedure | What it removes | Best when the problem is |
|---|---|---|
| Corpectomy | An entire vertebral body plus the discs beside it | Built into or behind the vertebral body, or the bone itself is damaged |
| Discectomy | Only the disc between two vertebrae | Confined to the disc, such as a herniated disc |
| Laminectomy | The lamina, the bony arch at the back of the vertebra | Pressure coming from behind the spinal canal |
| ACDF | A cervical disc, then a fusion from the front | Neck compression at the disc level |
| Kyphoplasty | Nothing; it stabilizes a fractured vertebra with cement | A compression fracture that has not compressed the cord |
A useful way to think about it: a discectomy clears the doorway between two vertebrae, a laminectomy lifts the roof off the back of the canal, and a corpectomy removes the whole pillar when the trouble is built into the bone. For the head-to-head detail, see our comparisons of corpectomy and discectomy, corpectomy and laminectomy, corpectomy and ACDF, and kyphoplasty and corpectomy. Often the choice is not one versus another in theory but which one fits the exact spot and cause in front of the surgeon, and sometimes two are combined in a single operation.
Source: University of Maryland Medical System: corpectomy patient guide | Columbia Neurosurgery: corpectomy overview
Risks and What Recovery Looks Like
Any spine operation carries risk, because the spinal cord, nerve roots, and nearby structures sit in a small, delicate space. The reassuring part is that, across large reviews of spine surgery, serious complications are uncommon. The most detailed data comes from anterior cervical spine surgery, the most common setting for a corpectomy, where difficulty swallowing (dysphagia) is the most frequent issue and is usually mild and temporary.
Other reported issues in that same body of data are less common, including temporary C5 nerve weakness at 3.0%, nonunion of the fusion (pseudarthrosis) at 2.0%, hoarseness at 1.3%, a spinal fluid leak at 0.5%, and esophageal injury at 0.2%. The through-line is that outcomes track closely with how carefully the operation is planned and performed. This is surgery where the hands doing it matter, which is why surgeon training and experience belong near the top of any patient's questions.
Recovery is a gradual build rather than a single finish line. The surgical incision and soft tissues heal in the first weeks, while the bone fusion solidifies over many months.
Timelines vary with the region treated and the reason for surgery, and many patients feel largely recovered well before the fusion is fully solid. A brace or collar is common early on, short walks are encouraged, and strength returns with guided physical therapy, which Desert Spine and Pain arranges by referral. For the full risk and recovery detail, see the vertebral corpectomy guide.
Source: Journal of Spine Surgery: Complications of anterior cervical spine surgery, a systematic review | Spine-Health: anterior cervical corpectomy recovery
How to Get Started
If a corpectomy has been mentioned, the most useful next step is a focused evaluation that confirms whether the compression truly needs a corpectomy, or whether a smaller decompression, a discectomy, or non-surgical care could do the job. A thorough consult reviews your symptoms, your exam, and your actual images together, and it is the right time to ask about alternatives and to get a second opinion before any major spine surgery.
Desert Spine and Pain is a Phoenix, Arizona practice led by Dr. David L. Greenwald, MD, FACS, and it draws patients from across the Greater Phoenix area and beyond for complex spine care. Care always starts with the least invasive effective option and escalates to surgery only when it is genuinely the best path. Procedures are performed by Dr. Greenwald at affiliated surgical facilities.
Learn about corpectomy at Desert Spine and Pain
Book a consultation or second opinion
Common Questions About Corpectomy
Is a corpectomy major surgery?
What conditions does a corpectomy treat?
What is the difference between a corpectomy and a discectomy?
Where in the spine can a corpectomy be done?
What is recovery from a corpectomy like?
Related Spine Terms
- Cervical corpectomy: the neck-specific version, done from the front and fused as an ACCF.
- Discectomy: removal of a disc only, used when the problem is confined to the disc space.
- Laminectomy: decompression from the back of the spine by removing the bony arch, sometimes paired with a corpectomy.
- ACDF: anterior cervical discectomy and fusion, which removes a disc rather than a vertebral body.
- Spinal fusion: joining two or more vertebrae into one solid unit, the stabilizing half of a corpectomy.
- Kyphoplasty: a minimally invasive repair for some compression fractures, a less extensive option than removing the vertebra.
- Myelopathy: spinal cord dysfunction from compression, a frequent reason for a corpectomy.
- Strut graft and cage: the bone graft or implant that bridges the gap left when a vertebral body is removed.
Sources
Sources and Methodology
This guide summarizes established clinical references and peer-reviewed data on corpectomy and anterior cervical spine surgery. Complication rates are pooled figures for anterior cervical spine procedures, the most common setting for a corpectomy, and are presented as general reference, not as individual predictions. Recovery ranges are general guides that vary by spinal region and the reason for surgery. This is educational information, not medical advice. Decisions about surgery should be made with a qualified spine surgeon after an in-person evaluation.
- American Academy of Family Physicians: Cervical Spondylotic Myelopathy
- Columbia Neurosurgery: Thoracic Corpectomy
- University of Maryland Medical System: Cervical Corpectomy Patient Guide
- Journal of Spine Surgery (2020): Complications of Anterior Cervical Spine Surgery, a Systematic Review
- Spine-Health: Anterior Cervical Corpectomy Procedure



