
What Is a Corpectomy? Procedure, Recovery, and How Long It Takes
Corpectomy, in plain terms: A corpectomy is spine surgery that removes an entire vertebral body, plus the discs beside it, to relieve pressure on the spinal cord or nerves. The surgeon rebuilds the gap with a bone graft or cage and fuses the segment with hardware. It can be done in the neck, mid-back, or lower back.
If a surgeon has raised the idea of a corpectomy, two questions usually come first: what exactly does it involve, and how long will it take? The word itself is a clue. "Corpus" means body and "ectomy" means to remove, so a corpectomy removes the body of a vertebra, the main block of bone that makes up most of each spinal segment. It is the operation chosen when whatever is pressing on the spinal cord is built into the bone itself, out of a disc surgery's reach, or when a vertebra has been damaged by a fracture, tumor, or infection. This guide walks through how the procedure works, how long the operation and the recovery actually take, how it differs from a discectomy, and the real risks.
- A corpectomy removes a full vertebral body (and the neighboring discs) to decompress the spinal cord or nerves, then rebuilds and fuses the spine with a graft or cage and hardware.
- The operation is done under general anesthesia and is more extensive than a single-level discectomy, so it usually runs longer; exact time scales with the number of levels and the spinal region.
- Hospital stay varies by region: many neck (cervical) patients go home the next day, while mid-back (thoracic) stays commonly run about three to seven days.
- Early recovery is roughly six to eight weeks, and the fusion typically shows healing on imaging by around three to six months, then keeps solidifying for several more months.
- It is used when compression or damage sits in the vertebral body itself: multilevel stenosis with myelopathy, large bone spurs, a hardened ligament, a retrovertebral disc, fracture, tumor, or infection.
What's in This Guide
How a Corpectomy Works
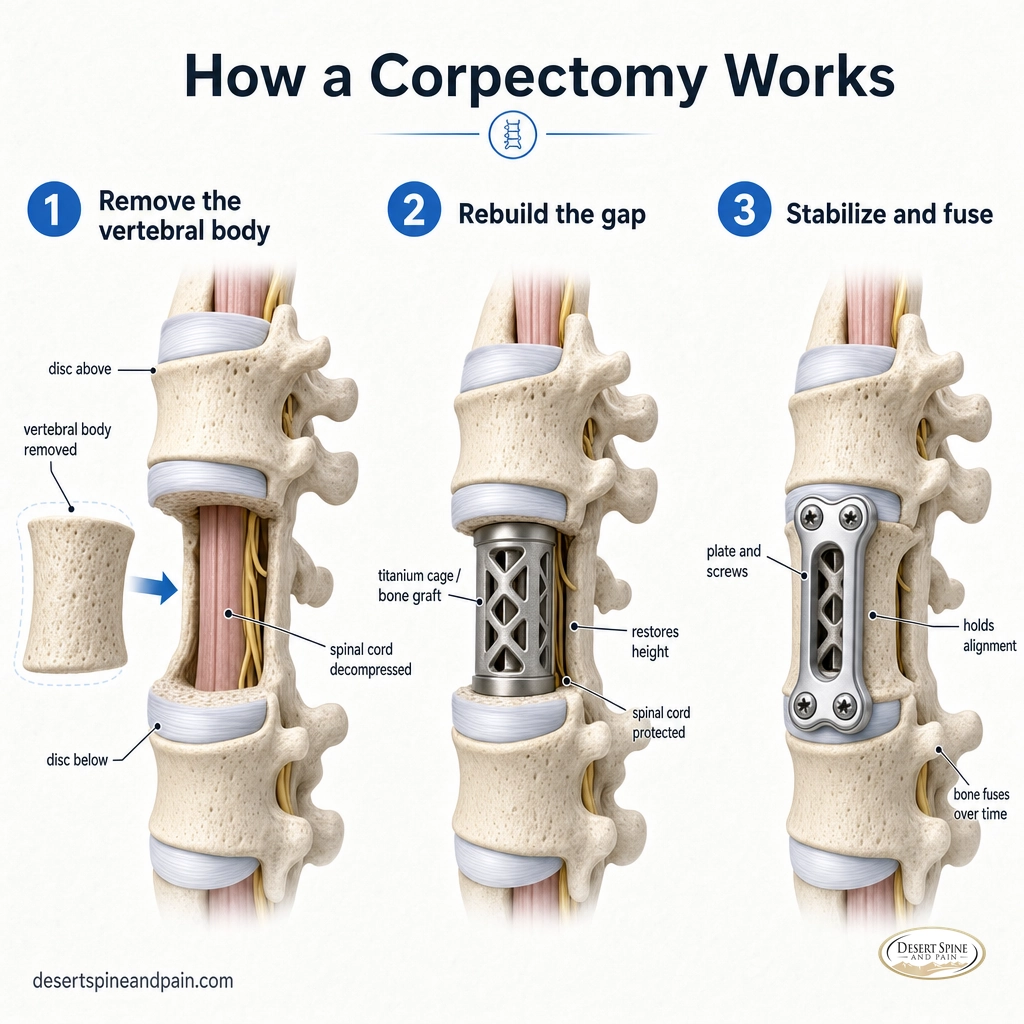
Wherever it is performed on the spine, a corpectomy follows the same logic: reach the vertebral body, remove it along with the discs above and below, clear away whatever is pressing on the neural structures, then rebuild the gap and fuse the segment. The surgical approach (from the front, side, or back) changes with the region, but the core sequence stays the same.
- Anesthesia and positioning. You are placed under general anesthesia and positioned so the surgeon has a safe, direct path to the affected level.
- The approach. The surgeon opens a protected corridor to the spine, moving muscles and other structures aside and shielding nearby arteries and nerves. In the neck this is usually from the front; in the mid or lower back it is often from the front or side.
- Removing the vertebral body. Using imaging to confirm the exact level, the surgeon removes the discs on either side and then the vertebral body itself, along with any bone spurs, hardened ligament, disc fragments, tumor, or infected bone sitting against the spinal cord or nerves. This is the decompression.
- Rebuilding the gap. Removing a vertebral body leaves a space that has to be filled. The surgeon bridges it with a strut of bone (from the patient or a donor) or a titanium or synthetic cage packed with graft material.
- Stabilizing with fusion. Hardware (a plate, or screws and rods) is fixed across the segment to hold everything steady while the bone grows together. Over months, the graft and the neighboring vertebrae fuse into one solid unit.
Because a corpectomy both takes pressure off neural structures and permanently joins the treated segment, it solves two problems in one operation. A helpful way to picture it: the surgeon removes a damaged pillar, clears the space behind it, sets a new pillar in place, and braces it until the bone heals around it. The practice performs this through its corpectomy decompression service, often alongside a reconstruction.
Source: University of Maryland Medical System corpectomy patient guide | Columbia Neurosurgery corpectomy overview
Why a Corpectomy Is Done
At Desert Spine and Pain, the philosophy is the least invasive effective treatment first, and most spine problems never need surgery at all. A corpectomy becomes the right tool only when a vertebral body is the source of the problem, either by pressing on the spinal cord and nerves or by being so damaged that it has to be removed. The usual reasons include:
- Multilevel spinal stenosis with myelopathy. When degenerative narrowing and bone spurs compress the spinal cord across more than one level, a corpectomy can decompress the whole span at once.
- Large bone spurs (osteophytes) that project from the back of a vertebral body into the spinal canal.
- A hardened posterior longitudinal ligament, where the ligament behind the vertebral bodies turns to bone and presses on the cord.
- A disc fragment that has migrated behind the vertebral body, out of reach of a standard discectomy.
- Fracture, tumor, or infection that has destroyed or invaded the vertebral body and must be removed to relieve pressure and restore stability.
The degenerative cord compression a corpectomy often addresses in the neck, cervical spondylotic myelopathy, is described in the medical literature as the most common spinal cord disorder in adults over 55 in North America. Wear-and-tear changes on imaging are extremely common, though, and do not on their own mean surgery is needed.
That is why a careful, in-person evaluation matters. The decision to remove a vertebral body rests on your symptoms, your neurological exam, and your imaging read together, never on a scan alone. For the full range of problems that can lead here, see the Desert Spine and Pain overview of spine conditions.
Source: American Academy of Family Physicians: Cervical Spondylotic Myelopathy | Columbia Neurosurgery: indications for corpectomy
How Long Does a Corpectomy Take?
"How long does a corpectomy take?" has two very different answers, and it helps to separate them. One is the length of the operation itself. The other, and the one that matters more day to day, is how long recovery takes.
The operation itself
A corpectomy is done under general anesthesia and is more involved than a single-level discectomy, because a whole vertebral body is removed and the spine is then rebuilt and fused. For a sense of scale, a comparable anterior cervical discectomy and fusion (ACDF) generally takes one to three hours, and a corpectomy usually runs longer than that. There is no single fixed number: operative time rises with the number of levels being treated, the region of the spine, and whether the reconstruction is done from the front, the side, or a combination. Your surgical team gives you a specific estimate once the plan is set.
Source: Mayfield Clinic: anterior cervical discectomy and fusion operative time
Recovery, step by step
Recovery is a gradual build, not a single finish line. Two things happen at once: the incision and soft tissues heal in the first weeks, while the bone fusion solidifies over many months. Knowing which is which keeps expectations realistic. Timelines vary with the region treated and the reason for surgery, so the ranges below are general guides.
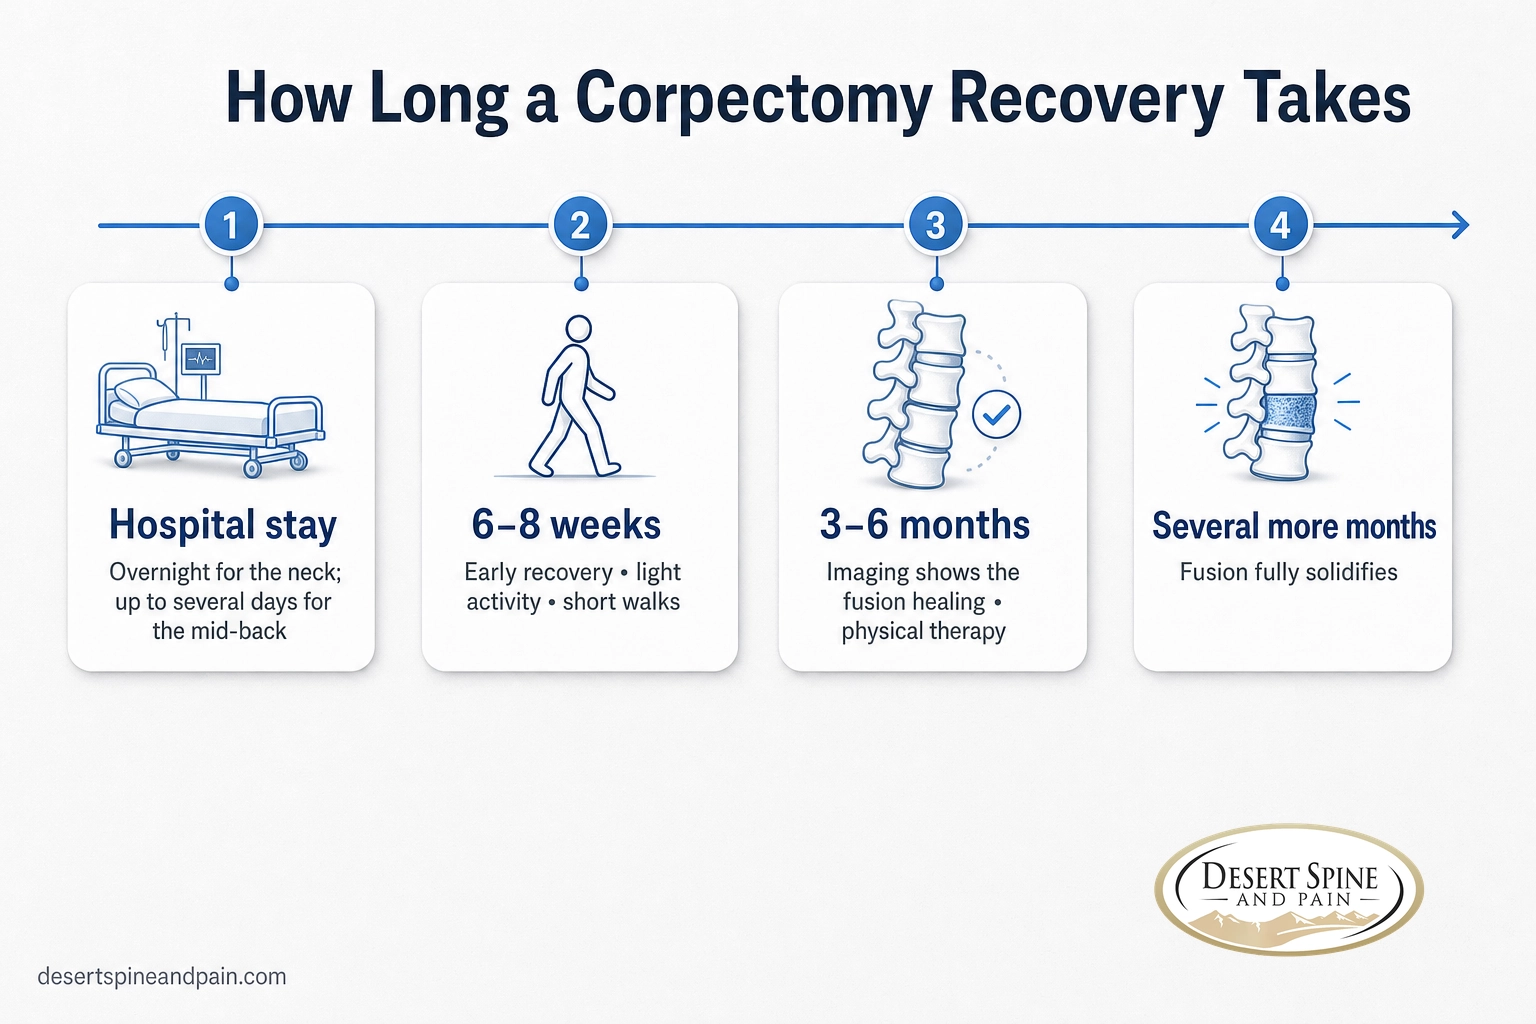
- Hospital stay. This depends on the region. Many neck (cervical) patients stay overnight and go home the next day. Mid-back (thoracic) reconstructions are larger, and hospital stays there commonly run about three to seven days. A brace or collar is often used for the first several weeks.
- First six to eight weeks. This is the typical early recovery window. Activity is kept light, with limits on heavy lifting, bending, and twisting while the graft settles. Short walks are encouraged early.
- Three to six months. Strength and stamina keep returning, often with guided physical therapy arranged by referral. Follow-up imaging usually shows the fusion healing as expected in this window.
- Several more months. The graft continues to set up until the treated segment becomes one solid unit, which takes longer than feeling back to normal.
Because the fused segment no longer bends, patients often worry about losing movement. In practice, a one or two-level fusion removes only a small share of total motion in most regions, and the healthy segments above and below take over, so day-to-day movement usually stays functional. Columbia Neurosurgery notes that for a thoracic corpectomy there are generally no long-term limitations from the procedure once healing is complete.
Source: University of Maryland Medical System recovery notes | Columbia Neurosurgery: thoracic corpectomy recovery

Corpectomy vs. Discectomy
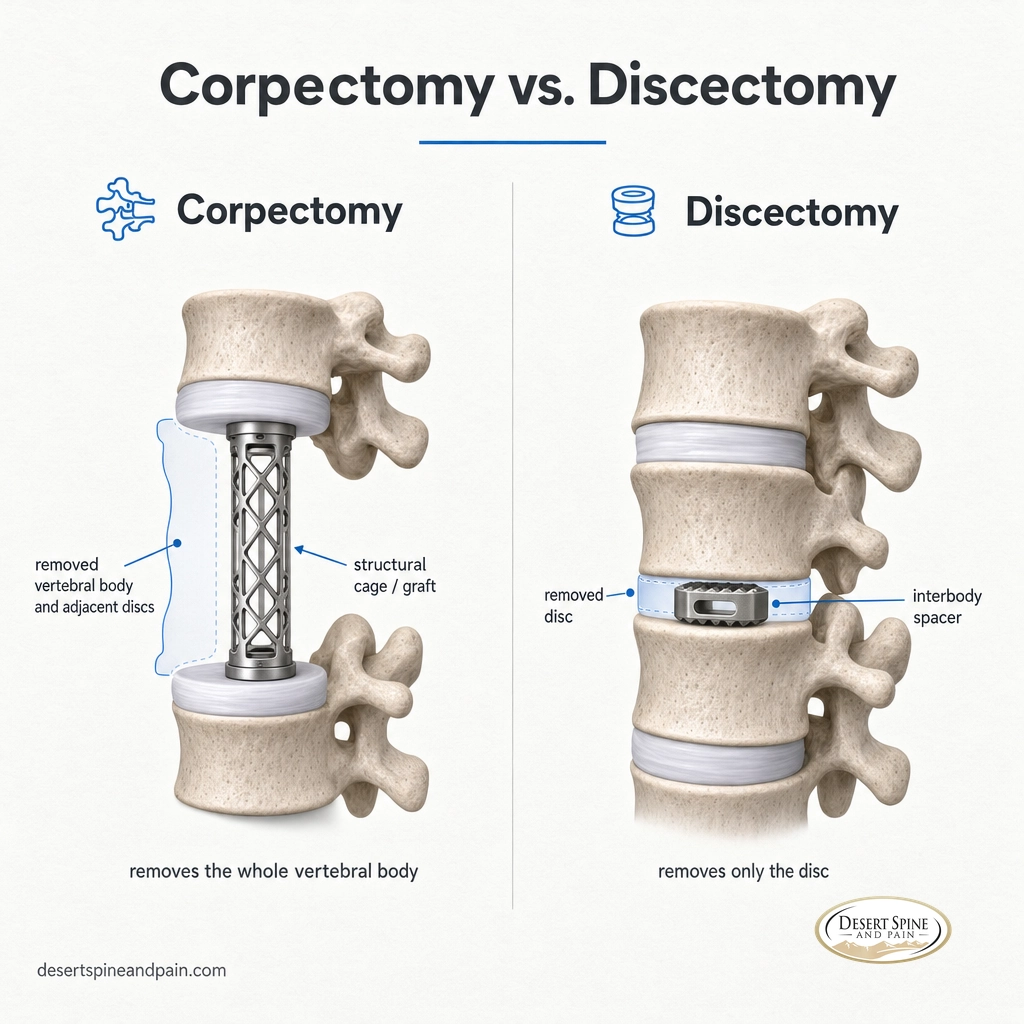
The single most common point of confusion is how a corpectomy differs from a discectomy. Both can be done from the front of the spine and both usually end in a fusion, so they are easy to mix up. The difference is what gets removed, and that comes down to where the pressure is.
| Feature | Corpectomy | Discectomy |
|---|---|---|
| What is removed | An entire vertebral body plus the discs beside it | Only the disc between two vertebrae |
| Best when the pressure is | Behind or within the vertebral body (bone spurs, hardened ligament, retrovertebral disc, fracture, tumor) | At the disc level only |
| Span covered | One corpectomy covers about the same span as a two-level discectomy | One disc space per level treated |
| Reconstruction | A single strut graft or cage bridging the gap, plus hardware | A spacer in each disc space, plus a plate |
A useful way to think about it: a discectomy clears the doorway between two vertebrae, while a corpectomy removes the wall itself when the problem is built into the bone. Surgeons often choose a discectomy and fusion when the compression is confined to the disc spaces, and reach for a corpectomy when disease sits directly behind the vertebral body or spans several levels. In some cases the two are combined in a single operation.
Myth: "A corpectomy and a discectomy are the same thing." They are not. A discectomy leaves the vertebral bodies in place and removes only disc tissue. A corpectomy removes a whole vertebral body. Assuming they are interchangeable leads patients to underestimate both what the surgery addresses and what recovery involves.
Source: University of Maryland Medical System corpectomy patient guide
Risks and Complications
Any spine operation carries risk, because the spinal cord, nerve roots, and nearby structures sit in a small, delicate space. The reassuring news is that, across large reviews of spine surgery, serious complications are uncommon. The most detailed complication data comes from anterior cervical spine surgery, the most common setting for a corpectomy. The chart below shows pooled rates from a systematic review covering hundreds of thousands of anterior cervical procedures.
Reported complication rates after anterior cervical spine surgery
Pooled incidence across anterior cervical spine surgery, the most common setting for a corpectomy. Source: Journal of Spine Surgery (2020), Yee, Swong, and Park.A few points help put these numbers in context. Difficulty swallowing is the most common issue, and in most patients it is mild and temporary: chronic swallowing trouble lasting beyond three months was reported in under 1% of cases in the pooled retrospective data. C5 palsy, a weakness usually of the shoulder, typically recovers over weeks to months. Nonunion, where the fusion does not fully take, is more likely in multilevel reconstructions and in smokers, which is why surgeons are strict about avoiding nicotine during healing.
The through-line is that outcomes track closely with how well the operation is planned and performed. This is surgery where the hands doing it matter. Dr. David L. Greenwald, MD, FACS is board certified as both a spine surgeon and a neurosurgeon, and that dual training is built around exactly this kind of delicate cord decompression. When the compression is less extensive, a minimally invasive approach may be an option.
Source: Journal of Spine Surgery: Complications of anterior cervical spine surgery, a systematic review
Types of Corpectomy by Spine Region
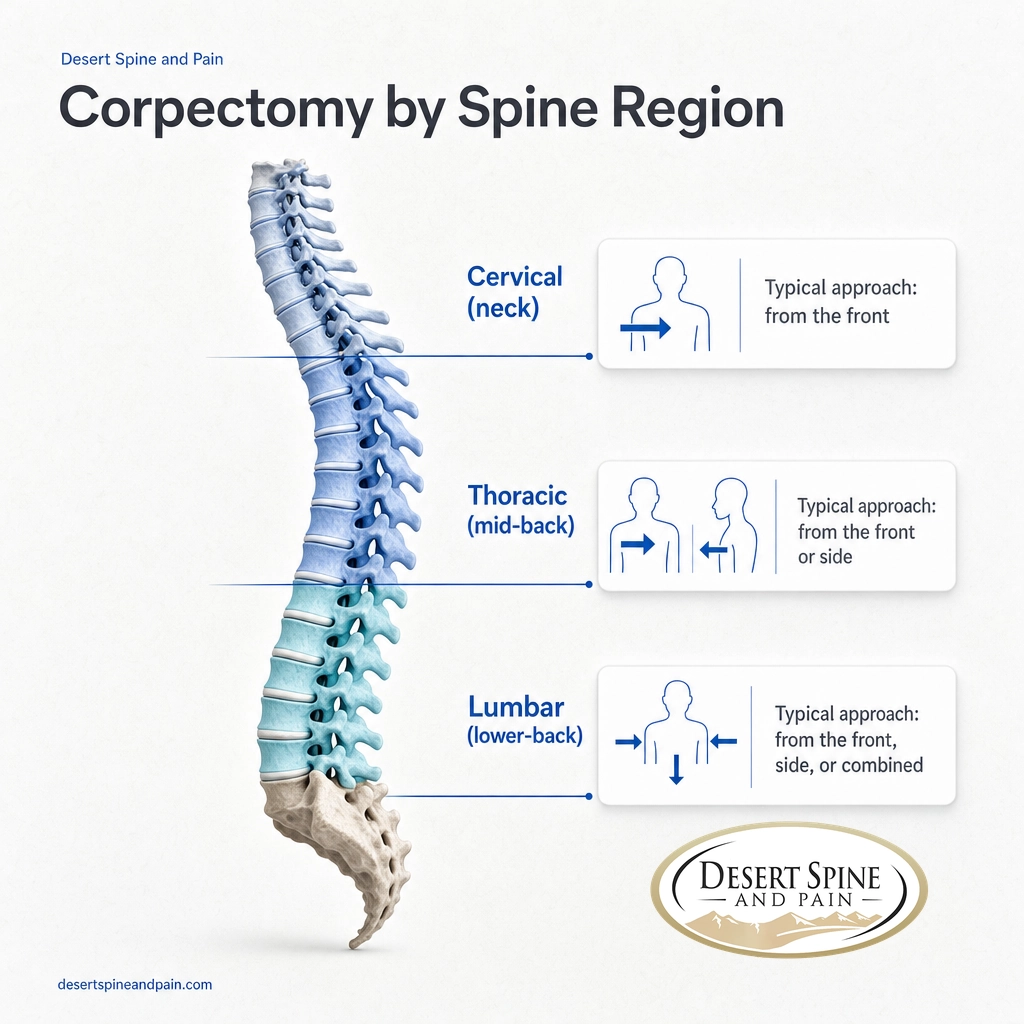
"Corpectomy" is a family of operations rather than one fixed procedure. The same core steps apply wherever it is done, but the region of the spine shapes the approach, the reconstruction, and the most common reason for surgery.
| Region | Where | Typical approach | Common reasons |
|---|---|---|---|
| Cervical | Neck | Usually from the front (anterior) | Multilevel stenosis with myelopathy, bone spurs, hardened ligament, retrovertebral disc |
| Thoracic | Mid and upper back | Often from the front or side | Fracture, tumor, infection, degenerative compression |
| Lumbar | Lower back | Front, side, or combined | Burst fracture, tumor, infection, severe degeneration |
The cervical spine is the most common setting for a corpectomy, because degenerative narrowing and cord compression are frequent in the neck. For the neck-specific version, including the anterior approach and how it compares with an ACDF, see our detailed guide to how a cervical corpectomy works. For a deeper look at the operation across all regions, including its full purpose and how the spine is rebuilt, see our guide to the vertebral corpectomy procedure and purpose. In every region a corpectomy pairs decompression with a fusion, which is why it is sometimes combined with a decompression from the back of the spine for very tight or multilevel compression.
Source: Columbia Neurosurgery: thoracic corpectomy | Desert Spine and Pain stenosis surgery options
How to Get Started
If a corpectomy has been mentioned, the most useful next step is a focused evaluation that confirms whether the compression truly needs a corpectomy, or whether a smaller decompression, a discectomy, or non-surgical care could do the job. A thorough consult reviews your symptoms, your exam, and your actual images together, and it is the right time to ask about alternatives and to get a second opinion before any major spine surgery.
Desert Spine and Pain is a Phoenix, Arizona practice led by Dr. David L. Greenwald, MD, FACS, and it draws patients from across the Greater Phoenix area and beyond for complex spine care. Care always starts with the least invasive effective option and escalates to surgery only when it is genuinely the best path. Procedures are performed by Dr. Greenwald at affiliated surgical facilities.
Learn about corpectomy at Desert Spine and Pain
Explore spinal fusion and reconstruction options
Book a consultation or second opinion
Common Questions About Corpectomy Surgery
How long does a corpectomy surgery take?
How long does it take to recover from a corpectomy?
Is a corpectomy major surgery?
What is the difference between a corpectomy and a discectomy?
How long will I stay in the hospital after a corpectomy?
Related Spine Terms
- Vertebral corpectomy: the all-regions procedure in depth, including its full purpose and how the spine is rebuilt.
- Cervical corpectomy: the neck-specific version, done from the front and fused as an ACCF.
- ACDF: anterior cervical discectomy and fusion, which removes a disc rather than a vertebral body.
- Spinal fusion: joining two or more vertebrae into one solid unit, the stabilizing half of a corpectomy.
- Laminectomy: decompression from the back of the spine by removing the bony arch, sometimes paired with a corpectomy.
- Kyphoplasty: a minimally invasive repair for some compression fractures, a less extensive option than removing the vertebra.
- Myelopathy: spinal cord dysfunction from compression, a frequent reason for a corpectomy.
Sources
Sources and Methodology
This guide summarizes established clinical references and peer-reviewed data on corpectomy and anterior cervical spine surgery. Operative-time context is drawn from published figures for a comparable anterior cervical fusion; a corpectomy is more extensive and generally takes longer, and actual time varies by region and number of levels. Complication rates are pooled figures for anterior cervical spine procedures, the most common setting for a corpectomy, and are presented as general reference, not as individual predictions. Recovery and hospital-stay ranges are general guides that vary by spinal region and the reason for surgery. This is educational information, not medical advice. Decisions about surgery should be made with a qualified spine surgeon after an in-person evaluation.
- University of Maryland Medical System: Cervical Corpectomy Patient Guide
- Columbia Neurosurgery: Thoracic Corpectomy
- Mayfield Clinic: Anterior Cervical Discectomy and Fusion (ACDF)
- American Academy of Family Physicians: Cervical Spondylotic Myelopathy
- Journal of Spine Surgery (2020): Complications of Anterior Cervical Spine Surgery, a Systematic Review



